New Zealand is paying more to end lives than care for them

By | Recent News

A frontline New Zealand GP has exposed a troubling financial incentive at the heart of our end-of-life system — assisted dying pays up to six times more than palliative care. According to an article in Doctor NZ, Fiordland Medical Practice specialist GP Stephen Hoskin has written to Deputy Prime Minister David Seymour, raising urgent questions about why the system is structured this way, and who is responsible for fixing it.

The numbers are stark. Under his PHO, Dr Hoskin can claim $517.50 per patient for providing palliative care in the community. This covers every visit, every call, every hour spent supporting a dying person and their family. By contrast, the Te Whatu Ora website indicates a GP could claim up to $3,080 for a single assisted death. This isn’t a technical error either. This is a system that has been built (unintentionally or not) to reward ending lives over supporting them.

This isn’t a claim from a lobby group. It’s the assessment of a working rural doctor. Dr Hoskin describes the situation as “deeply concerning and unethical,” warning that even well-meaning doctors carry unconscious biases. When a patient raises assisted dying, and a doctor knows they could earn six times more by proceeding rather than redirecting towards palliative care, can we truly say that the consultation is unbiased? Dr Hoskin doesn’t think so, and neither should we.

The rural health disparities make this worse. Some palliative care visits in rural New Zealand are reimbursed at under $50 — less than the cost of a standard GP consultation, and a fraction of what urban patients may receive. Why doesn’t a dying person in Fiordland deserve the same quality of end-of-life support as someone in Wellington?  Despite the Government spending $119 million on hospice care for 2025/26, these disparities persist.

Before the End of Life Choice Act was passed, and again during its three-year review, pro-life advocates and organisations, including Family First NZ, warned that financial disparities and perverse incentives would follow. Those concerns were dismissed as scaremongering. Well, it looks like this recent exposure by Dr Hoskin confirms what we have always said — the system is not neutral. It structurally incentivises death over palliative care, and it has been doing so since the Act came into force in November 2021.

And it appears from the deflection in responses from Seymour to the Health Minister to Te Whatu Ora, no one is taking accountability for a system that Dr. Hoskin describes as “deeply concerning and unethical. While Te Whatu Ora recognises that palliative care funding is “inconsistent across New Zealand” and mentions a National Palliative Care Work Programme but provides no timeline or specific commitments.

Three deflections. Zero answers. Nobody owns this.

And the push to expand the system continues regardless. A proposed amendment bill, lodged by ACT’s Todd Stephenson, wants to make it easier for doctors to raise assisted dying directly with patients — removing one of the few remaining safeguards in the current legislation. Even more troubling, the bill includes removing the 6-month prognosis time-limit and looks to pressure palliative care facilities to participate in assisted dying services. Organisations built around the sanctity of life and caring for the dying could be compelled to facilitate death instead. Combined with the financial incentives already baked into the system, this expansion should alarm every New Zealander who cares about protecting the elderly, the vulnerable, and the dying.

A society’s priorities are revealed by what it funds. Right now, New Zealand is paying more to end lives than to cherish them.

Source: New Zealand Doctor Rata Aotearoa. All quotes and figures cited are drawn from their original reporting.


Check out our euthanasia factsheet

 

France pushes to open the door to euthanasia

By | Recent News

Yesterday, the French National Assembly voted on passing a bill legalising assisted dying. This marks the next phase in a year-long debate on euthanasia and assisted dying. The National Assembly voted in favour of the bill to legalise assisted dying in May 2025, but the French Senate rejected it and sent it back for further reconsideration about eight months later. Iterations to the bill have been made since, with the debate returning to the French parliament earlier in Jan, and a final vote held on Feb 25th. The final vote on the bill was 299 in favour and 226 against, with an absolute majority set at 263. Ironically, the accompanying bill on palliative care was also unanimously passed at the same time.

With steps closer to legalising assisted dying, the euthanasia bill adopts the assisted dying model, making self-administration of the lethal substance the rule and assistance from a third party the exception if the individual is unable to self-administer. This would only be available to those who meet strict eligibility criteria, which require them to be over 18 years of age, residing in France, and suffering from a life-threatening incurable illness in a terminal stage. Individuals will also need to express their wish to end their lives. If this sounds familiar, that’s because we’ve seen the same course of action here at home.

Currently, the Léonetti Law of 2005 regulates end-of-life care, permitting individuals to refuse “futile medical care” and to access palliative treatment. In 2016, the Claeys-Léonetti Law expanded these provisions, allowing deep and continuous sedation until death under specific conditions, applicable when the patient suffers unbearably and death is deemed inevitable and imminent.

Olivier de Margerie, the president of Accompanying Life Until Death, is concerned that presenting assisted suicide as an individual liberty risks pressuring people with terminal illnesses. Mr. de Margerie argues that:

“introducing the possibility of ending one’s existence — where society organises and facilitates the process — is a direction that will, in the fairly short term, lead to a reduction in the financial, political and technical efforts to develop palliative care that is available everywhere and accessible to everyone in France.”

He’s right. Once the state normalises assisted suicide and society accepts it as normal and routine healthcare, investment in compassionate alternatives inevitably declines.

Australian bioethicist and author Xavier Symons also cautions that lawmakers in different countries considering euthanasia might underestimate how eligibility criteria could broaden over time. He notes:

“The biggest risk is establishing a ‘right to die’ that could extend far beyond terminal illness, thus allowing access to euthanasia to any group that wants it,” he said. “This includes people with mental illness, people with chronic illnesses, and even people tired of life. If it is claimed that some people have the right to euthanasia, it is difficult to deny the conclusion that all people have the right to euthanasia.”

And this is the exact pattern we are seeing in different jurisdictions like France’s neighbours, the Netherlands and Belgium, and let’s not forget Canada, where assisted suicide (they call it medical assistance in dying) is the 5thleading cause of Canadian deaths. Not forgetting that each of these countries often begins with restrictions on assisted suicide, only for expansion to follow slowly and quite drastically.

Now, whilst the French National Assembly just passed the bill again, overriding the Senate’s earlier rejection and sending it back to the Senate, which is largely conservative. But the pressure to adopt euthanasia is intensifying, and France is yet another nation on the brink of institutionalising and normalising the idea that the sanctity of life only matters for some and not others.

France’s debate will be a crucial one to follow. It highlights how rapidly a society can move from defending life to enabling death—and underscores the importance of consistently advocating for genuine compassion, true dignity, and quality palliative care, rather than state-approved killing.

*Written by Family First writers*

Ethos Alliance: ACT’s euthanasia law would breach human rights

By | Recent News

ETHOS ALLIANCE PRESS RELEASE


ACT wants to expand euthanasia but this would breach fundamental human rights in the New Zealand Bill of Rights Act.

“ACT’s changes breach human rights and take away freedom of choice,” says Alex Penk, author of a new report for MPs on the End of Life Choice Amendment Bill. “The Bill would stop doctors and care facilities like hospices from using their conscience and making ethical decisions like they do now.”

“Assisted dying is already highly controversial and most doctors don’t want to be involved,” says Penk. “The Bill would introduce euthanasia for long-term conditions and disabilities, like chronic heart conditions, frailty, diabetes, renal failure, multiple sclerosis, and motor neurone disease. This would force doctors and care facilities into more conscience conflicts. Doctors have to use ethical judgment all the time but the Bill sends a message that they’re just supposed to do what the state tells them. There’s a real risk it’ll force ethically-minded people out of medicine.”

“ACT’s bill would also undermine palliative care. It would cover ‘care facilities’, including hospices, disability support facilities, and rest homes. Care facilities would have to be prepared to allow assisted dying even when that goes against their beliefs. Facilities like hospices do an incredible job for vulnerable people but they’re over-stretched and under-funded. They shouldn’t be backed into a corner if they don’t want to be involved in euthanising their residents.”

“This is not what Kiwis voted for,” says Mr Penk.  “David Seymour said that conscience is a cornerstone of the law, and 65 percent of voters supported that law in a referendum. There is no mandate to change such a fundamental part of the law. Let individual doctors and care facilities decide if they want to offer assisted dying, or the government could just do a better job of providing information.”

“It’s ironic that a law about end-of-life choice would limit freedom of choice,” says Penk. “MPs will get a conscience vote if the Bill goes before Parliament. Why shouldn’t doctors and care facilities get to use their conscience too?”

END

For more info check out: https://www.ethosalliance.nz/news-and-views

The slippery slope of organ donation and assisted dying

By | Recent News

In an opinion piece (in response to a Stuff NZ article on organ donations and assisted dying), Dr John Kleinsman of the Nathaniel Centre for Bioethics argues against combining organ donation with assisted dying in New Zealand, despite organ shortages. He highlights concerns around coercion, emphasizing the societal pressure that could make vulnerable people feel compelled to choose assisted dying or face societal expectations.

While doctors can legally refuse to participate in assisted dying, those on organ retrieval teams are inevitably connected to the process of ending life. He points out that, although the public might see ending a patient’s life and organ retrieval as separate, in practice, the medical teams must work closely together. Essentially, the organ retrieval team, whether they consent or not, will play a role in how the patient dies, making them inherently connected with the act of directly, intentionally, and prematurely ending a patient’s life. This threatens the conscientious objection rights of doctors who entered medicine to save lives, not end them, and may even exclude doctors from minority ethnic or religious backgrounds who are uncomfortable with assisted dying.

Organ recipients won’t be told if their donor died through assisted dying, which violates their autonomy. Dr Kleinsman notes that 35% of New Zealanders opposed assisted dying in the 2020 referendum, making transparency about donor circumstances crucial for respecting recipients’ right to make informed decisions.

Dr Kleinsman argues that while organ donation is normally a generous gift, the utilitarian argument of increasing organ supply by the likes of Organ Donation New Zealand (ODNZ) isn’t a sufficient justification when weighed against these ethical concerns.

*Written by Family First staff writers*

Please see here for the original article and Dr Kleinsman’s full response.
Check out our Family Matters episode with Dr. John Kleinsman

Euthanasia has surged to become one of Canada’s top killers

By | Recent News

The report indicates that cancer, especially lung, colorectal, pancreatic and blood cancer, was the most frequently reported condition in nearly all age groups of people who died by MAID in 2024, except those 85 and older, “for whom ‘other’ conditions were the most frequently cited.

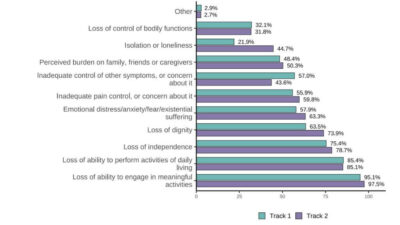
Interestingly, inadequate pain control was only the sixth most common reason for seeking MAID. The primary reasons for euthanasia deaths were related to autonomy and daily function:

  • Loss of ability to engage in meaningful activities (the highest reason, over 95% for both tracks).
  • Loss of ability to perform activities of daily living.
  • Loss of independence and loss of dignity

Figure: Reported nature of suffering, by track

Source: Sixth annual report: Medical assistance in dying Canada

In terms of MAID deaths across districts, Quebec has the highest number of euthanasia deaths at 5,998.  MAID deaths remain heavily concentrated in three provinces, which accounted for nearly 85% of all provisions: Quebec (36.4%), Ontario (4,944 deaths, 30.0%) and British Columbia (2997 deaths, 18.2%).

Nearly all MAID deaths were performed by a doctor or nurse practitioner. While the law allows patients to self-administer the medication in most parts of the country (except Quebec), this option is rarely chosen. The typical (median) age of a person receiving MAID in 2024 was about 78 years old. Recipients who were near the end of their lives (Track 1) had a median age of 78.0 years, while those whose death was not immediately foreseeable (Track 2) were slightly younger, with a median age of 75.9 years. Overall, the average age of MAID recipients continues to rise slightly each year.

There was a notable increase in track 2 euthanasia deaths, which increased by 17% accounting for 4.4% of total euthanasia deaths and up from 4.1% in 2023. Track 2 euthanasia deaths refer to not immediately foreseeable deaths of people and are more likely not to have a terminal condition, to be women, younger and living with a disability.

Dissecting Track 2 euthanasia deaths a little further, it appears people who die by Track 2 euthanasia deaths are significantly more likely to be poor, live in institutions or poor neighborhoods, and be receiving disability support services than those who die under Track 1. Of the 16,104 people who responded to questions around disabilities, roughly one-third (32.9 per cent) reported having a disability.

Alex Schadenberg, chair of the Euthanasia Prevention Coalition (EPC), suggests that MAID for non-terminal conditions mainly targets individuals with disabilities, noting a clear link between disability and Track 2 deaths, as 61.5% of Track 2 recipients identify as disabled.

If that isn’t shocking enough, loneliness and isolation were reported as a factor in 44.7% of Track 2 deaths and 21.9% of Track 1 deaths, suggesting that over 3,800 people listed this as a primary reason. Track 2 recipients were far more likely to be receiving mental health/social support services (31.4%) compared to Track 1 recipients (9.4%), indicating that mental health is a prevalent factor in non-terminal MAID cases.

These statistics are both disturbing and tragic, highlighting pro-life advocates’ concerns about expanding Canadian euthanasia laws to include non-terminal individuals. These vulnerable groups are often affected by factors such as lower socioeconomic status, disabilities, and insufficient social support. The recent MAID data confirms this, showing that social and systemic problems—like loneliness and inadequate disability support—are significant factors influencing requests for MAID.

The most concerning finding in the 2024 Annual Report is not only the total number of MAID deaths but also the speed at which this peak was reached. Despite the growth rate slowing to 6.9% in 2024, this follows years of swift expansion that propelled Canada from having a recently legalized system to becoming a global leader in euthanasia deaths. This trend confirms that MAID is shifting from a last-resort service to a major—and quickly becoming a leading cause of death in Canada.

*Written by Family First writers*

Simon O’Connor: Speaking to the House of Lords on Euthanasia

By | Recent News

This week I found myself up at 4am to speak to the House of Lords in the United Kingdom.  As you may know, they are considering yet another euthanasia/assisted suicide Bill and the Lords are currently holding committee hearings and wanted to know of the New Zealand experience.

There were four of us in total, two supporting life and palliative care and two that either support or lean in support of euthanasia.  I was there alongside Professor Sinead Donnelly, a professor and palliative medicine physician. Naturally, I’m with Family First, but I was also there, having chaired the health committee in parliament when it then undertook the largest ever inquiry, that into euthanasia.

I will admit, it was both a very early and long morning.  The way the House of Lords operates means that just about every vote requires the Lords to be there in person, so bells would ring during the hearing, and they would have to leave!

My message to the Lords was simple – euthanasia laws inevitably expand.  There was a sense from some of the Lords (those in support of euthanasia) that their UK law would be exceptional, that, unlike other countries, their proposed law would be complete and never need to be changed.

I simply pointed out that every jurisdiction that introduces euthanasia laws sees expansion.  I pointed out that we are only three years in here in New Zealand, and already, there is a big push to expand the law.  To remove conscience rights from doctors, nurses, and hospices; to let doctors promote euthanasia to patients; for the Ministry of Health to advertise euthanasia; and to remove the likely 6 months to live requirement.

The key dynamic in play, that I attempted to succinctly explain to the Lords, was the euthanasia moves swiftly from being a health issue to a justice issue.  Debate begins around terrible medical conditions (think neurological disorders such as Huntington’s disease) but swiftly moves to one about rights, not discriminating, and equal access.

I was also at pains to point out the contradictory statements being made by the New Zealand pro-euthanasia witnesses.  On one hand, they were saying New Zealand’s law has important safeguards yet the very next minute they were saying that safeguards are an obstruction and prohibition that should be removed.  Quite extraordinary!

A particularly memorable moment, which elicited loud gasps from the Lords present, was when one of the pro-euthanasia researchers here in New Zealand stated:

“The concerns about palliative care being undermined are more about the palliative care professionals who cannot sit with their own discomfort about assisted dying”

You can appreciate why there were gasps to this dismissive and dangerous statement.  What was being strongly stated is that any moral or ethical concerns around terminating people should be put aside; that palliative care practitioners with concerns should be dismissed.  This New Zealand researcher also appears blind to why people might experience such discomfort, and doubly so when it’s those in palliative care who spend their lives trying to help the dying live well to the very end.

Let’s hope that the Lords see the value of life and vote no to this proposed law.

The dangerous path of euthanasia expansion

By | Uncategorized

The inevitable has happened, with the ACT Party and other pro-euthanasia/assisted suicide proponents calling for the expansion of the system.  Euthanasia has been legal for barely three years, and over 1200 Kiwis have ended their lives, and already proponents want more.

Three plus years ago, we were told by euthanasia proponents that there was no slippery slope or push to expand, and that few New Zealanders would take it up.  1200 deaths later, and a push for a new Members’ Bill in the name of ACT MP Todd Stephenson tells us a very different story.

We were also told that the system would be safe.  It is not.  As I write, we know of a tragic case where a non-English speaking woman with dementia was euthanised, despite no translator being present.  There is also at least one euthanasia case now before the police.

Those put in charge of reviewing euthanasia cases noted that forms were not poorly filled out, and that what doctors were saying about their patients did not match what was written on the forms.  These reviewers also questioned the lack of information provided to them, and ultimately, as these reviewers asked more questions – and became whistleblowers – they had their roles cancelled (ironically, by the author of the End of Life Choice Act and now government Minister, David Seymour).

We also know that Health New Zealand cannot even give New Zealanders accurate numbers of deaths.  Its reports frequently get numbers wrong, in one instance, missing nearly half the number of people who died in one quarter.

All this to say, the current system is not working well, and mistakes are happening.

We also know that very few doctors and nurse practitioners want to be part of the service.  Around 120 are involved, from a pool of 20,000.  The response by euthanasia proponents and Todd Stephenson is to remove conscience rights of doctors and nurses to object.  You have read that right – a law based on autonomy wants to remove autonomy from medical professionals.  The same is true for hospices, with the proposed amendment wanting to force their facilities to allow euthanasia, even though it is the antithesis of palliative care.  Autonomy for some, coercion for others!

We also have recent research from Auckland University that noted the main reason people seek euthanasia is fear of losing control of their lives.  While clearly underlying health issues, it was people’s fear of future suffering and death that drove the requests.  This was further emphasised by the doctors who noted that the ‘unbearable suffering’ criteria is totally subjective.

The same research also, distressingly, highlighted the experience of one doctor being surprised when a patient did not die quickly and instead gagged, choked, and struggled to breathe after orally ingesting lethal drugs.

Despite the rhetoric of a peaceful death, it is not always the case.  Just like the reporting mistakes, the inability to objectively identify suffering, and the already simple processes being ignored, Todd Stephenson and others are pushing for an expansion.

They point to Canada, and yet this country’s approach to euthanasia should be a warning. Euthanasia in Canada is now the 5th leading cause of death, alongside the likes of cerebrovascular diseases (think the likes of strokes) and chronic lower respiratory diseases (think the likes of emphysema and chronic bronchitis).  One in twenty, or 5%, of Canadians now die by euthanasia.  Euthanasia was billed as something rare, and proponents continue to provide the ‘next hard case, ’ but it is clear it expands and expands.  Sticking with Canada, they have even changed the law to allow mental illnesses (though it is yet to take effect) and are discussing euthanising babies and children.

A final observation.  Proponents of euthanasia continue to couch their language in terms of compassion and love.  Let’s be clear, euthanasia and assisted suicide have nothing to do with ‘compassion’ or love.  Quite the opposite.  Compassion literally means to suffer with; it does not mean to eliminate the sufferer (which ironically, is more often those watching a loved one die, not the loved one).  And love seeks to provide hope and care, not removal.

*Written by Family First staff writers